


Description of the potential effects of thymosin beta fragment 4 (1-4)(Ac-SDKP) based on the literature. (This is not a product description, disclaimer at the bottom of the page)
Ac-SDKP (N-acetyl-seryl-aspartyl-lysyl-proline) is a very small protein fragment derived from another natural protein called thymosin β4. In the body, special enzymes cut thymosin β4 into smaller pieces, and one of the results of this process is Ac-SDKP [1]. This small molecule is important because it helps protect organs from scarring (fibrosis), which occurs when too much stiff tissue builds up after injury or disease. The problem is that Ac-SDKP does not last very long in the body
- is rapidly broken down by an enzyme called ACE (angiotensin-converting enzyme). Interestingly, ACE-blocking drugs (such as some hypertension drugs) can increase Ac-SDKP levels by up to five times, enhancing its protective effect [1].
Initially, scientists thought that Ac-SDKP's main role was to keep blood stem cells from growing too fast. However, more recent studies show that its larger role is in tissue healing and protection. It helps to stop excessive proliferation of scar tissue in organs such as the heart, lungs, liver and kidneys. For example, it reduces the activity of certain signals that cause cells to produce too much collagen (the main protein of scars) and prevents repair cells (fibroblasts) from turning into scar-forming cells. In the case of kidney disease, Ac-SDKP shows real promise. Not only does it help the kidneys to function better, but it also reduces scarring by blocking the access of too many immune cells and alleviating the harmful processes that usually make damage worse. In short, Ac-
SDKP acts as a natural 'anti-scarring' and 'tissue-protecting' molecule in the body. It promotes healing, reduces inflammation and can be useful in the treatment of diseases in which scarring and tissue damage play an important role.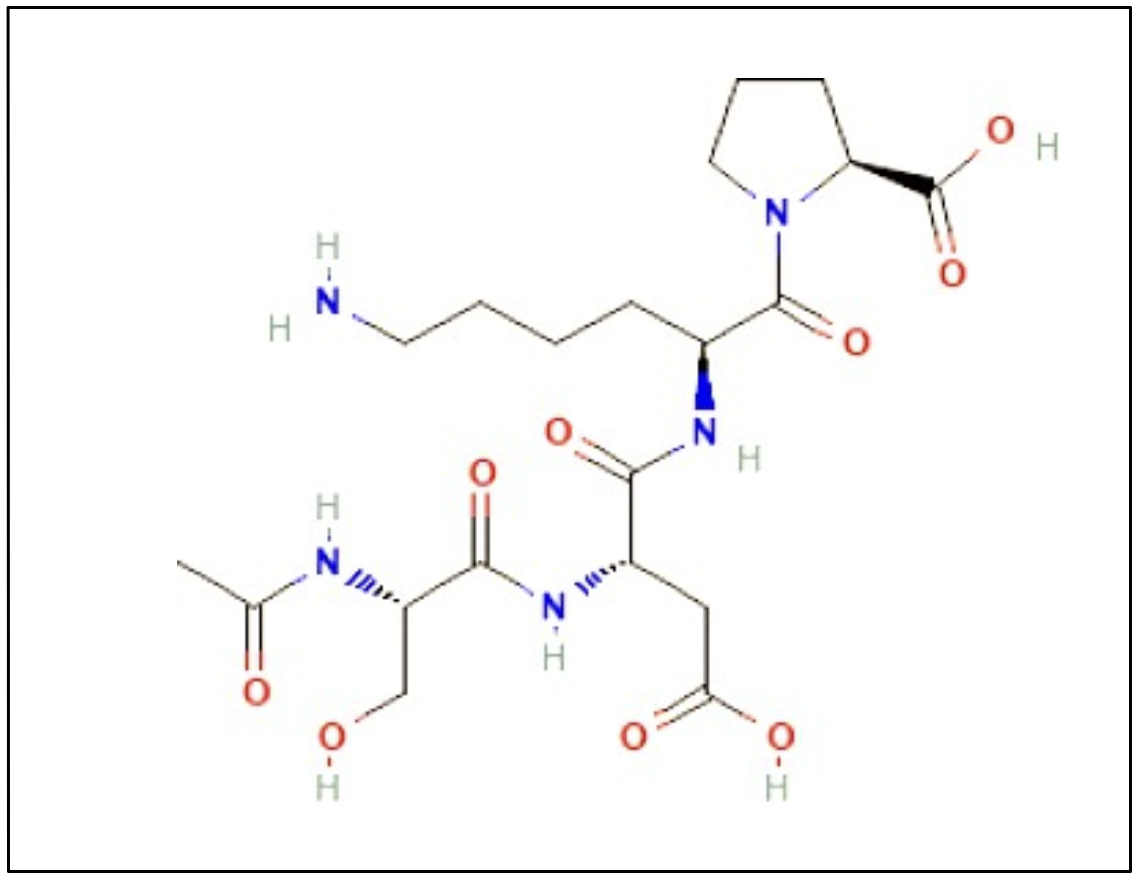
Ac-SDKP protects the heart (based on animal studies)
Several scientific studies have described the potential of Ac-SDKP for heart health in both emergency and long-term problems. In a mouse model of myocardial infarction, Nakagawa et al. administered Ac-SDKP at a dose of 1.6 mg/kg/day via a small subcutaneous pump and found clear benefits: heart wall tears (heart ruptures) fell from 51.0% to 27.3%, and mortality fell from 56.9% to 31.8%. The peptide appeared to work by calming 'first-helper' immune cells that can exacerbate damage (M1 macrophages), while not altering helpful repair macrophages (M2) or neutrophils. It also slowed the action of an enzyme (MMP-9) that breaks down heart tissue after infarction, while another marker (MPO) was unchanged, suggesting a targeted, intentional action [2]. In the case of cardiac scarring caused by prolonged high blood pressure, Peng et al. showed that Ac-SDKP could reduce existing scar tissue, not just prevent it. In rats with a well-established model of hypertension, daily administration of Ac-SDKP at a dose of 400-800 µg/kg (subcutaneously) for 8 weeks reduced the amount of collagen in the heart - the main sign of scarring - in a dose-dependent manner (the higher dose was more effective). Blood pressure per se did not fall, and normal responses to angiotensin I and bradykinin were unaffected, so the benefit was not solely due to a reduction in blood pressure. Blood levels of Ac-SDKP increased 2-5-fold, and key 'scar-inducing' signals in the heart (TGF-β and CTGF) were reduced, confirming a direct anti-scarring effect [3].
After myocardial infarction, persistent swelling and scarring can lead to heart failure. Yang et al. tested Ac-SDKP both early (to prevent damage) and later (to reverse damage). In both cases, total cardiac collagen content decreased (for example, from ~24 to ~15 µg/mg in the prevention group and from ~23 to
~14 µg/mg in the reversal group). The deleterious accumulation of immune cells was also reduced: macrophages decreased by about a third in each group, and TGF-β-positive cells decreased in parallel. These benefits were achieved without lowering blood pressure or reducing the size of the heart, and pumping power was not markedly improved in the prophylaxis group. Nevertheless, the steady decrease in scarring and inflammation indicates an improvement in cardiac structure over time [4].
Ac-SDKP may also explain some of the 'additional' tissue benefits observed with ACE-inhibiting drugs. Rasoul et al. compared a model of angiotensin II-induced hypertension with groups receiving captopril or Ac-SDKP (400-800 µg/kg/day). This raised blood levels several-fold and reproduced many of the protective properties similar to ACE inhibitors: less cellular hypertrophy in the heart, fewer macrophages and mast cells, lower levels of TGF-β and CTGF, and less collagen accumulation. Importantly, these benefits occurred without lowering blood pressure or reducing cardiac thickening, indicating a
direct protective effect on cardiac tissue [5]. Ac-SDKP slows scar formation in the heart at the cellular level. In cultured rat cardiac support cells (fibroblasts) in the laboratory, Rhaleb et al. tested very low doses of Ac-SDKP (0.05-100 nmol/l) and found two key effects: a reduction in cell growth (DNA copying) to normal at around 1 nmol/l and a reduction in collagen (the main 'scar' protein) produced in response to endothelin-1, a potent scarring signal. Lower doses worked best for collagen; very high doses were less effective. The peptide appeared to silence a common cellular signal switch (p44/42 MAPK/ERK), and a known MAPK blocker provided the same benefit. Put simply, Ac-SDKP commands fibroblasts to slow down both proliferation and excessive scar formation, presumably by reducing the activity of a key growth pathway [6].
In addition, it protects the heart from galectin-3-induced damage. In a study in adult rats, Liu et al. administered galectin-3 (a protein that induces inflammation and scarring) for four weeks and observed more inflammatory cells, thicker heart walls, more severe scarring around vessels and between cells, higher levels of TGF-β/Smad3 signalling (a pathway that promotes scarring) and weaker pumping on echocardiography. The addition of Ac-SDKP (800 µg/kg/day) prevented most of these changes: inflammatory cells, scarring and thickening of the heart wall decreased, and cardiac function improved. Data suggest that it protects the heart by turning off the TGF-β/Smad3 'scarring switch' and mitigating inflammation [7]. In addition, it reduces cardiac scarring in long-term hypertension without changing blood pressure itself. Using a classical vascular model (2 kidneys, 1 clamp) in rats, Rhaleb et al. administered Ac-SDKP (400 µg/kg/day, subcutaneously). Although blood pressure and cardiac hypertrophy remained elevated, treatment with the peptide significantly reduced both inflammatory and proliferating cells in the myocardium. Importantly, it normalised the interstitial collagen fraction, reducing it from about 10.1% in hypertensive rats to about 5.4%, a level almost identical to that in control animals (≈5.3%). In short, it reduced the deleterious tissue lesions even when the pressure load remained unchanged, suggesting a direct role in tissue healing [8]. Additionally, in combination with thymosin-β4, Ac-SDKP promotes tissue repair after myocardial infarction. In a narrative review, Cavasin et al. found that thymosin-β4 promotes both cell migration and survival. Its derivative, Ac-SDKP, provides additional benefits by acting as an anti-fibrotic agent in hypertension. In models of myocardial infarction, Ac-SDKP was shown to reverse scar formation and reduce inflammation. It also promoted angiogenesis, as shown in both in vivo and ex vivo studies. In addition, Ac-SDKP reduced the risk of cardiac wall rupture in mice, highlighting its therapeutic potential in cardiovascular repair. There is a lot of overlap in benefits, suggesting that Ac-SDKP carries part of the therapeutic effect of thymosin β4. However, the researcher mentioned that human studies are still needed to confirm these laboratory results and animal studies [9].
In addition, Ac-SDKP reduces the activity of tissue degrading enzymes triggered by IL-1β. In adult rat heart fibroblasts, Rhaleb et al. showed that interleukin-1β (IL-1β), a pro-inflammatory cytokine,
significantly increased the expression of matrix metalloproteinases (MMP-2, MMP-9 and MMP-13). These enzymes degrade components of the extracellular matrix and contribute to adverse remodelling. Ac-SDKP did not alter the basal expression of MMPs. However, it strongly inhibited the IL-1β-induced increase in the levels of these enzymes. At the same time, Ac-SDKP increased the expression of tissue inhibitors of metalloproteinases (TIMP-1 and TIMP-2), natural inhibitors of MMP activity. This helped to rebalance matrix turnover. Ac-SDKP also reduced the activation of two major signalling pathways that drive inflammation and proliferation: NF-κB and ERK/MAPK. Interestingly, IL-1β stimulation did not increase collagen production in this model. Ac-SDKP also had no effect on collagen synthesis. This suggests that its protective role is due to selective rebalancing of tissue remodelling, rather than a general change in collagen production. Taken together, these results indicate that Ac-SDKP may protect the myocardium from pathological remodelling by rebalancing matrix regulation [10].
Ac-SDKP protects against autoimmune cardiac damage in rats. In a model of T-cell-induced myocarditis, Nakagawa et al. treated immunized Lewis rats with Ac-SDKP and observed preservation of cardiac function, both systolic and diastolic. The treatment also reduced cardiac enlargement, reduced scar formation and preserved a healthier myocardial structure. Histological analysis showed a lower number of infiltrating immune cells, including macrophages, dendritic cells and T lymphocytes. In parallel, levels of key inflammatory mediators including cytokines (IL-1α, TNF-α, IL-2, IL-17), chemokines (CINC-1, IP-10), adhesion molecules (ICAM-1, L-selectin) and matrix metalloproteinases were significantly reduced. Interestingly, Ac-SDKP did not alter the levels of myosin-specific autoantibodies or antigen-specific T-cell responses. This indicates that its cardioprotective effect is primarily due to a reduction in immune cell recruitment and inhibition of inflammatory mediators, rather than a change in autoantibody production or T-cell activation [11].
Ac-SDKP reduces inflammation and collagen cross-link formation in angiotensin II-induced hypertension. González et al. administered angiotensin II to rats for three weeks, and a separate group was treated with Ac-SDKP. Blood pressure and cardiac hypertrophy remained elevated in both groups, but Ac-SDKP prevented the increase in both total collagen and cross-linked collagen. This protective effect was due to the inhibition of lysyl oxidase (LOX) mRNA and LOXL1 protein, enzymes responsible for collagen cross-linking and scar stiffening. In addition, Ac-SDKP reduced TGF-β expression, inhibited NF-κB activation and reduced infiltration of CD4⁺ and CD8⁺ T lymphocytes and CD68⁺ macrophages into cardiac tissue. Importantly, the influx of CD4⁺ T cells correlated with LOXL1 expression, suggesting a mechanistic link between immune cell activity and fibrosis. These findings highlight that Ac-SDKP exerts potent anti-fibrotic and anti-inflammatory effects independently of its effects on blood pressure [12].
In addition, it protects the heart after myocardial infarction in mice in the early and late stages. Peng et al. administered Ac-SDKP (1.6 mg/kg/day) to C57BL/6J mice after myocardial infarction. In the first week, treatment reduced the number of lethal wall ruptures, decreased ICAM-1 levels, reduced macrophage influx and gelatin digestion activity, inhibited p53 and reduced myocardial cell death; at the same time, the number of small blood vessels at the edge of the injury increased, suggesting better new vessel growth. At week five, hearts showed less interstitial collagen, preserved structure, lower levels of endoplasmic reticulum stress (CHOP) and maintained SERCA2 (crucial for calcium metabolism), as well as overall better function. In short, it reduces early damage and promotes healthier long-term remodelling [13].
In another study, Ac-SDKP reduces cardiac scarring and improves diastolic function in diabetic cardiomyopathy. Castoldi et al. induced diabetes in rats and two months later started Ac-SDKP (1 mg/kg/day with minipumps) for eight weeks. Rats with diabetes developed high sugar levels, marked interstitial and perivascular fibrosis and higher TGF-β1 and phospho-Smad2/3 levels in the heart. Ac-SDKP reduced both types of fibrosis and reduced TGF-β/Smad signalling, also in animals receiving the ACE inhibitor ramipril. Cardiac ultrasound showed that diabetes impaired systole and diastole; insulin and ramipril restored both functions, while Ac-SDKP partially improved diastole (diastolic function). These data highlight the antifibrotic benefit with a moderate increase in function in this model [14]. In addition, it protects the coronary vessels from radiation damage and preserves blood flow. In a rat model with thoracic irradiation, Sharma et al. administered Ac-SDKP subcutaneously for 18 weeks. Radiation reduced resting blood flow, killed endothelial cells, increased coronary fibrosis and disrupted tight junction proteins (claudin-1, JAM-2). This restored blood flow to normal, preserved endothelial cells, reduced fibrosis and restored tight junctions. Laboratory studies showed that Ac-SDKP penetrates endothelial cells and reduces radiation-induced reactive oxygen species levels; in live animals, the labelled peptide concentrated in endothelial cells within hours. These results indicate vascular protection, less oxidative damage and better microvascular integrity after irradiation [15]. In addition, it reduces stress-induced scar formation in cardiac support cells. In human cardiac fibroblasts, cells were pretreated with Ac-SDKP (10 nM) and then treated with tunicamycin (0.25 µg/ml), which causes 'protein stress' inside the cell factory (endoplasmic reticulum). Ac-SDKP helped to stop stressed cells from producing too much collagen. It worked by calming the cellular response to stress, reducing the activity of a stress protein called CHOP and decreasing the activity of an inflammatory switch called NF-κB. It also lowered levels of IL-6, the signal that triggers inflammation. When CHOP was genetically reduced, it continued to decrease NF-κB and type I collagen activity at both the protein and mRNA levels, confirming the same pathway [16]. Put simply: under stress conditions, this helps cells to avoid excessive scar protein production.
In addition, it reduces the inflammation of the vessel lining induced by TNF-α. In human coronary artery endothelial cells, TNF-α stimulation induced a significant increase in the expression of ICAM-1. This adhesion molecule plays a key role in promoting leukocyte adhesion to the blood vessel surface. Pretreatment with Ac-SDKP significantly reduced ICAM-1 levels in a dose-dependent manner. Mechanistic analysis showed that this effect was mediated by inhibition of the IKK → IκB → NF-κB signalling cascade, which is crucial for the activation of inflammatory gene expression. Interestingly, two other signalling pathways, p38 MAPK and ERK, were unaltered, indicating that Ac-SDKP selectively interacts with the NF-κB pathway to exert anti-inflammatory effects in endothelial cells [17]. Ac-SDKP helps to keep the vascular lining quiescent and reduces its 'stickiness' during inflammation. In addition, it prevents scarring of large arteries in angiotensin II-induced hypertension, even without lowering the pressure itself. In angiotensin II-treated rats, Ac-SDKP reduced collagen accumulation in the aorta and reduced signals (mRNA of type I and III collagen) that cause scarring. It also reduced protein kinase C overactivity, oxidative stress, ICAM-1 and macrophage entry into the vessel wall. Fibrosis signals decreased (less TGF-β1 and Smad2 activity), while the natural inhibitor of this pathway (Smad7) increased. Blood pressure and aortic thickness remained high, so these benefits to the vessel wall were due to direct tissue effects rather than pressure changes [18].
Ac-SDKP also protects the heart from radiation damage. In rats that received targeted thoracic radiation, 18 weeks of Ac-SDKP preserved cardiac function, reduced extracellular matrix accumulation and fibrosis, reduced macrophage influx and decreased cardiac cell death. The level and release of Mac-2 (galectin-3), a macrophage protein responsible for fibrosis, also decreased. Ac-SDKP was observed inside macrophages near the cell nucleus and prevented the radiation-triggered release of Mac-2; when fibroblasts lacked Mac-2, radiation caused much weaker scarring signals [19]. It helps maintain healthier vasculature and cardiac tissue after irradiation by reducing inflammation and scar formation.
Ac-SDKP for lung health (based on animal studies)
Ac-SDKP showed more potent antifibrotic effects than thymosin-β4 in lung models. First, in laboratory studies using lung cells from people with idiopathic pulmonary fibrosis (IPF), it slowed excessive cell growth and reduced two TGF-β-induced fibrosis signals: α-SMA and collagen. Meanwhile, in mice given bleomycin to induce lung injury, thymosin-β4 helped at an early stage (day 7) by reducing inflammation and early scarring, but did not stop fibrosis at later stages (day 14-21). These findings suggest that Ac-SDKP blocks the primary stages of scarring in cells and may provide more stable and longer-lasting anti-fibrotic benefits than its precursor, thymosin-β4 [20]. In addition, it inhibits silica-associated lung scarring by restoring KIF3A and turning off β-catenin signalling
. In silicosis in particular, KIF3A levels were low in patient samples and in rat lungs. When KIF3A was restored, the activity of β-catenin and its downstream drivers MRTF-A and SRF decreased, thereby slowing the epithelial-to-myofibroblast transition (EMyT) associated with scarring. This consistently increased KIF3A function and consequently decreased β-catenin/MRTF-A/SRF signalling. However, once KIF3A was eliminated, Ac-SDKP lost these benefits, confirming that KIF3A is essential for its anti-fibrotic action [21].
In another study, Ac-SDKP in combination with VIP attenuated COPD-related changes caused by cigarette smoking in mice. It reduced oxidative damage (lower levels of MDA), scarring (lower levels of hydroxyproline) and a key driver of fibrosis (lower levels of TGF-β). At the same time, inflammatory cytokines (TNF-α, IL-1β, IL-6) decreased and antioxidant protection improved (higher SOD activity). Correspondingly, lung tissue under the microscope showed less inflammation and less structural remodelling. The combination of these substances provided antioxidant, anti-inflammatory and anti-fibrotic benefits in a model of smoke injury [22, 23]. Ac-SDKP also showed significant results in both the prevention and treatment of bleomycin-induced pulmonary fibrosis. In CD-1 mice, Ac-SDKP (0.6 mg/kg, i.p.) administered from day 0 or Day 7 improved survival and reduced bleomycin-related weight loss. In addition, the lungs showed less swelling and fewer invasive immune cells, healthier tissue structure and less fibrosis: both collagen staining and soluble collagen levels decreased. Mechanistically, pro-fibrotic IL-17 and TGF-β signals decreased, and α-SMA decreased, indicating fewer myofibroblasts. Importantly, benefits occurred in both early (prophylactic) and delayed (therapeutic) schedules [24]. Furthermore, it reduces silicosis-induced pulmonary fibrosis through the P-HSP27/SNAI1 pathway. In rats, silicosis caused an increase in P-HSP27, SNAI1, α-SMA and collagen I/III in lung tissue. In contrast, Ac-SDKP - administered either before exposure or after disease onset - decreased all of these markers and reduced the number of cells positive for both P-HSP27 and α-SMA on imaging. Importantly, its administration to healthy controls did not alter protein expression, suggesting that its effect is selective for diseased lungs [25].
In addition, it has shown strong antifibrotic effects in several animal studies. A meta-analysis including 18 randomised trials (428 animals, 2008-2021) found that Ac-SDKP reduced several fibrosis signals compared to untreated models: α-SMA (SMD -2.44), type I collagen (SMD -5.36), type III collagen (SMD -3.07), TGF-β (SMD -2.88) and pulmonary nodule area (SMD
-1.80); all P<0.001. Furthermore, hydroxyproline, a chemical readout of collagen, was also significantly altered [SMD 7.62; 95% CI 4.90-10.33; P=0.000], consistent with an effect on collagen turnover. These results indicate that Ac-SDKP consistently slows fibrosis in lung disease models [26]. In another study, it reduced TGF-β and CTGF levels, inhibiting silica-associated lung scarring in rats. Rats received silica to induce fibrosis, followed by prophylactic or therapeutic Ac-SDKP (800 µg/kg/day). Compared to the silicosis control group, TGF-β1 (to ~0.244 ± 0.016) and CTGF (to ~0.241 ± 0.017) protein levels were significantly reduced in the treated lungs. Similarly, mRNA levels
decreased and CTGF mRNA was notably lower compared to the model groups (P<0.05). In the prophylaxis group, both protein and mRNA for TGF-β1 were significantly below levels in the 8-week silicosis model (P<0.05). Finally, lung histology confirmed less fibrosis [27]. Furthermore, it inhibits collagen accumulation and improves lung structure in silicosis. Rats exposed to silicosis received Ac-SDKP either after injury (treatment) or 48 hours before exposure (prophylaxis). In the treatment groups, compared with the silicosis models, silicosis nodule area decreased to 84.28% and 67.93%, hydroxyproline to 70.89% and 58.18%, type I collagen to 71.08% and 58.13%, and type III collagen to 80.13% and 70.70% (at the respective time points). In the prophylactic groups, compared to the 8-week silicosis model, nodules decreased to 61,13%, hydroxyproline to 60,27%, and type I and III collagen to 40,13% and 65,77%. Correspondingly, HE and VG staining showed milder fibrosis. This reduced both collagen content and visible scarring [28].
Additionally, it protects the lungs and bones by calming macrophage pathways when exposed to silica. In rats and in cell models, silica activated TLR4 and RANKL, causing lung inflammation and bone resorption by osteoclasts. In contrast, Ac-SDKP treatment inhibited TLR4 and RANKL signalling, protected pulmonary elastin, reduced pulmonary inflammation and reduced macrophage activation. At the same time, in bone, Ac-SDKP blocked osteoclast differentiation and helped maintain bone density and microarchitecture. These results indicate a dual protection: healthier lungs and more stable bones in silica-related diseases [29]. It also reduces lung scarring by inhibiting the maturation of scar-forming cells. TGF-β1 normally stimulates lung support cells (fibroblasts) to transform into myofibroblasts and produce additional collagen. When Ac-SDKP was administered before TGF-β1, levels of α-SMA and collagen decreased, and levels of TGF-β1 and its receptor also decreased. Subsequently, in rats with silica-induced lung injury, administration of Ac-SDKP before or after exposure decreased TGF-β1 levels, RAS signals and SRF activity, and reduced the number of α-SMA-positive myofibroblasts in lung nodules. As a result, collagen accumulation decreased, demonstrating protection against fibrosis [30, 31]. Furthermore, Ac-SDKP protects the alveolar lining by preventing epithelial cells from transforming into scar-forming cells. Under the influence of damage signals such as silicosis and TGF-β1, epithelial markers (E-cadherin, SP-A) decrease, while mesenchymal and fibrosis markers (vimentin, α-SMA, collagen I/III) increase. With Ac-SDKP, this detrimental change was reversed: epithelial identity was preserved, fibrosis markers decreased and the TGF-β1/ROCK1 pathway was attenuated. Consequently, the delicate alveolar surface remained closer to normal and less prone to scarring [32]. Furthermore, it alleviates 'protein factory' stress and cell death in alveolar cells, which in turn reduces lung scarring. When silicosis strikes, cells show high ER stress signals (GRP78, phosphorylated PERK and eIF2α), CHOP and caspase-12, and many cells die. With Ac-SDKP - as well as the ER stress blocker 4-PBA - these stress markers decreased, cell death decreased in cell assays and in rats, and lung collagen decreased. Overall, by calming the PERK/eIF2α/CHOP pathway and caspase-12, Ac-SDKP helps protect the epithelial layer and slows the progression of fibrosis [33].
Ac-SDKP for kidney health (based on animal studies)
Ac-SDKP protects the kidneys in lupus without lowering blood pressure. Nakagawa et al (2017) showed that in lupus-prone NZBWF1 mice, it preserved renal filters (less glomerular sclerosis) and reduced overall damage without lowering systolic blood pressure. The onset of severe hypertension, urinary albumin and premature death occurred later with Ac-SDKP, but these delays were not statistically significant [34]. The substance also protects renal function during salt stress. Worou et al (2015) studied salt-sensitive Dahl rats that were treated with 800 or 1600 µg/kg/day for six weeks. Blood pressure continued to rise as a result of the salt diet, but the kidneys showed less inflammation, less fibrosis and healthier filters. Only the higher dose reduced urinary albumin levels in salt-sensitive rats. In the more resistant strain (SS13BN), both doses prevented albumin leakage and structural damage [35]. This indicates that the protective effect was independent of blood pressure. The peptide also reduces immune-mediated kidney damage in lupus. Liao et al (2015) found that at 20 weeks, treated lupus-prone mice had better kidney function, although lupus autoantibody levels were unchanged. The kidneys contained fewer invasive immune cells such as macrophages and T cells. Inflammatory signals such as cytokines and chemokines were lower, and activation of complement proteins (C5-9), RANTES, MCP-5 and ICAM-1 was inhibited. As a result, filtration function was preserved and microscopic damage was reduced [36].
In another study, it prevents hypertension-related kidney damage despite persistently high blood pressure. Rhaleb et al (2011) showed that in DOCA saline-treated mice, Ac-SDKP (800 µg/kg/day for 12 weeks) reduced renal scarring (collagen), filtration matrix expansion and monocyte/macrophage influx, while blood pressure remained elevated. Importantly, urinary albumin levels normalised - from 41 ± 5 µg to 13 ± 3 µg per 10 g body weight per day, approaching control levels - and the loss of nephrin (a key filtration gap protein) was partially restored [37]. Thus, Ac-SDKP protected the filtration barrier and reduced scarring regardless of blood pressure. In addition, it protects against scarring and diabetes-induced renal dysfunction. Shibuya et al (2005) showed that in db/db mice with type 2 diabetes, eight-week administration of Ac-SDKP via minipumps resulted in an approximately threefold increase in plasma Ac-SDKP concentration without any change in blood sugar levels. As a result, glomerular oedema, excessive mesangial matrix proliferation and extracellular matrix accumulation were prevented, and plasma creatinine levels approached normal. Albuminuria also decreased, although the decrease was not statistically significant. Mechanistically, it blocked Smad3 from entering the cell nucleus, thereby reducing TGF-β/Smad signalling associated with fibrosis [38]. Furthermore, Ac-SDKP reduces renal scarring in diabetes and is an additional benefit besides ACE inhibition. Castoldi et al (2013) induced diabetes in rats and then administered Ac-SDKP (1 mg/kg/day), ramipril (3 mg/kg/day), both drugs together or placebo. First, untreated diabetic rats developed high blood sugar levels, higher urinary albumin levels (albuminuria), renal fibrosis
renal fibrosis and reduced glomerular nephrin levels. With Ac-SDKP alone, renal fibrosis decreased but albuminuria did not improve. With ramipril, both albuminuria and fibrosis decreased and nephrin levels were restored. Importantly, the combination of Ac-SDKP with ramipril gave a greater reduction in fibrosis than ramipril alone, although albuminuria did not improve further. Ac-SDKP reduces fibrosis in diabetic nephropathy and enhances the anti-fibrotic protection of ACE inhibitors without additional benefit on albuminuria [39].
Interestingly, Zhang et al (2022) developed a bio-inspired dual-network hydrogel composed of gelatin and curcumin-zinc, coated with DOPA and functionalised with immobilised Ac-SDKP. This system was designed to overcome the limitations of free drugs, including poor solubility, absorption and stability. In vivo application in partially nephrectomised rat kidneys showed that the hydrogel consistently reduced local fibrosis, promoted angiogenesis and stimulated the formation of new renal tubules. Materials testing confirmed adequate porosity, mechanical strength and biocompatibility, further supporting its therapeutic potential [40]. Comparative studies also highlight the distinct and stage-dependent effects of thymosin-β4 (Tβ4). Zuo et al (2013) used models of unilateral ureteral obstruction in wild-type and PAI-1 gene-excluded mice to evaluate Ac-SDKP, Tβ4 and Tβ4 in combination with the prolyl oligopeptidase (POP) inhibitor. Ac-SDKP consistently reduced fibrosis in both genotypes, as demonstrated by lower collagen and fibronectin deposition, fewer activated myofibroblasts and macrophages and reduced pro-fibrotic signalling [41]. Furthermore, Wang et al (2010) showed that Ac-SDKP inhibited renal inflammation and obstruction-induced fibrosis. In rats with unilateral ureteral obstruction, 14-day treatment reduced tubulointerstitial scarring and inflammatory changes on histological examination. The peptide reduced renal macrophage infiltration (ED-1) and decreased MCP-1, NF-κB, α-SMA and TGF-β1 protein levels in tubular and interstitial cells. MCP-1 and TGF-β1 gene expression was also reduced, indicating that this reduced both inflammatory transport and extracellular matrix activation, which are key drivers of renal fibrosis [42]. Further evidence comes from models of hypertension with chronic renal damage. Liao et al (2010) administered Ac-SDKP at a dose of 800 µg/kg/day to rats after 5/6 nephrectomy, either before damage (prevention) or after damage (reversal). Despite persistent hypertension and left ventricular hypertrophy, treatment reduced albuminuria, reduced macrophage infiltration and reduced renal collagen levels in both groups. Loss of nephrin in the glomeruli was also partially preserved or restored, suggesting improved filtration barrier integrity. These findings highlight that the peptide provided renal protection in both early and advanced stages of the disease, mainly through anti-inflammatory and anti-fibrotic effects rather than through blood pressure control [43].
In aldosterone-salt hypertension, the peptide reduced scarring in both heart and kidney without affecting blood pressure. Peng et al (2001) studied rats with one kidney removed, which were
was given aldosterone and salt for six weeks. This treatment raised blood pressure, enlarged the heart and kidneys and increased scar tissue (collagen) along with cell growth markers (PCNA). Administration of Ac-SDKP, especially at the higher dose of 800 µg/kg/day, significantly reduced collagen and PCNA in a dose-dependent manner. Importantly, blood pressure and organ enlargement remained unchanged, while a lower dose (400 µg/kg/day) provided partial benefit [44]. In immune-mediated renal disease, the peptide improved renal function and reduced fibrosis. Omata et al (2006) treated rats with anti-GBM nephritis, starting 14 days after disease onset, with Ac-SDKP at 1 mg/kg/day for four weeks. Compared to untreated animals, it reduced urinary protein levels, decreased plasma urea and creatinine concentrations and improved creatinine clearance. Tissue analysis showed less glomerular sclerosis and interstitial fibrosis. Mechanistically, it decreased fibronectin, collagen and TGF-β1 levels, decreased Smad2 signalling, increased Smad7 and decreased macrophage accumulation in renal tissue [45]. In diabetes, the peptide blocked renal scarring by preventing blood vessel cells from transforming into scar-forming cells. Nagai et al (2014) showed that Ac-SDKP restored natural protective pathways, including let-7 microRNA and FGF receptor signalling, which were inhibited by diabetes. As a result, it reduced fibrosis and endothelial-to-mesenchymal transition (EndMT). Importantly, its combination with an ACE inhibitor improved renal protection even more than ACE inhibition alone [46].
In another study, the peptide restored healthy kidney metabolism and reduced fibrosis. Srivastava et al (2020) compared ACE inhibitors, ARBs, Ac-SDKP and their combinations in mice with diabetes. They also blocked its natural formation with a proline oligopeptidase inhibitor (POPi). The results showed that Ac-SDKP mediated the effects of ACE inhibitors by reprogramming renal metabolism: SIRT3 was restored, mitochondrial fatty acid oxidation was improved and abnormal glucose utilisation was reduced. In contrast, POPi reduced natural levels, accelerated fibrosis and disrupted metabolic balance. Importantly, ACE inhibitors (but not ARBs) partially restored its levels and reduced fibrosis. Both ACE inhibitors and Ac-SDKP reduced mesenchymal remodelling and decreased collagen I and fibronectin levels in diabetic kidneys [47].
In cancer therapy, the Ac-SDKP analogue helped to preserve blood cells during chemotherapy. Carde et al (1992) tested seraspenide in a double-blind, crossover phase I-II trial involving 53 patients receiving cytarabine or ifosfamide. Compared to control periods, patients treated with seraspenide had better protection of peripheral blood cells against chemotherapy toxicity. It was well tolerated and showed no adverse effects. These results suggest that Ac-SDKP-like peptides may protect the bone marrow during cytotoxic treatment [48]. In another study, the peptide did not reduce blood toxicity, but was safe. Cappelaere et al (1995) studied 84 patients with advanced squamous cell carcinoma receiving carboplatin and a continuous dose of 5-fluorouracil, along with
placebo or goralatide (Ac-SDKP) at a dose of 12.5 or 62.5 µg/kg/day. Over 221 cycles of chemotherapy, there were no differences in the lowest blood counts for leukocytes, granulocytes, platelets or haemoglobin between groups. The duration of toxicity also remained unchanged. However, anaemia and lymphopenia were more common with goralatide. Overall, the drug was well tolerated, but at these doses did not prevent chemotherapy-related blood cell loss [49].
In both type 1 and type 2 diabetes, the peptide improved scarring and renal function. Nitta et al (2016) treated CD-1 mice with streptozotocin-induced type 1 diabetes and db/db mice with type 2 diabetes with oral Ac-SDKP, imidapril (ACE inhibitor) or both drugs combined. Oral treatment, either alone or in combination, reduced glomerular sclerosis and tubulointerstitial fibrosis. Plasma cystatin C levels, which are elevated in renal disease, returned to normal levels. All therapies restored suppressed anti-fibrotic microRNAs (miR-29 and let-7), with the greatest improvement observed in the group receiving combination treatment. Urinary peptide levels were highest in the group receiving combination treatment, indicating improved systemic exposure [50]. For immune-mediated kidney disease, this reduced urinary protein levels and reduced inflammation and fibrosis. Tan et al (2012) administered MRL/lpr 1.0 mg/kg/day for 8 weeks to mice with lupus. Compared with untreated lupus mice, mice receiving the peptide had less proteinuria and better renal function. Renal tissue contained fewer infiltrating T cells and macrophages. Mechanistically, there was a reduction in NF-κB activation and TNF-α production, as well as a reduction in pro-fibrotic markers (TGF-β1, α-SMA and fibronectin). Phosphorylation of Smad2/3 was inhibited and Smad7 increased. Importantly, deposition of immune complexes and anti-dsDNA antibody levels were not altered, suggesting that the benefits were due to a reduction in inflammation and fibrosis rather than a change in antibody formation [51].
With obesity and high salt intake, it protected the kidneys by reducing inflammation, fibrosis and even blood pressure. Maheshwari et al. (2018) studied Zucker lean (ZL) and Zucker obese (ZO) rats fed normal salt (0.4%) or high salt (4%) for 8 weeks, with the ZO subgroup receiving a
1.6 mg/kg/day. High salt worsened renal inflammation and fibrosis in both groups, with obese rats showing the most severe macrophage infiltration (87.8 ± 10.8 versus 19.14 ± 1.5 cells/mm² in lean rats). Treatment reduced macrophage infiltration in obese rats to 32.18 ± 2.4 cells/mm² (P<0.05) and reduced glomerular sclerosis as well as interstitial fibrosis in both cortex and medulla (P<0.05). Systolic blood pressure in salt-fed obese rats also decreased from 164 ± 6.9 to 144.05
± 14.1 mmHg (P=0.004). Albuminuria was higher in obese rats than in lean rats, but was not significantly altered by salt intake or treatment [52].
Ac-SDKP for brain and nerve health (based on animal studies)
Protection in models of Parkinson's disease
This peptide helps protect dopamine-producing neurons and promotes better motor skills and memory in models of Parkinson's disease. Kamarehei and Zahednasab (2025) were the first to show in cell experiments that pre-treating SH-SY5Y nerve cells with 20 nM of this peptide protected them from 6-OHDA, a toxin commonly used to mimic Parkinson's disease. In rat studies, daily doses of 800 µg/kg after 6-OHDA brain damage preserved more dopamine neurons and reduced cell death by decreasing caspase-3 and caspase-12 activity. Treated rats also showed better motor coordination, improved spatial memory and fewer symptoms of anxiety and depression. Mechanistically, the benefits were due to reduced oxidative stress, alleviated endoplasmic reticulum (ER) stress and reduced inflammatory signals in the brain, which promotes neuronal survival and regeneration [53].
Regeneration after spinal cord injury
It also accelerates recovery and redirects inflammation towards healing after spinal cord injury. Hashemizadeh et al (2022) administered 0.8 mg/kg subcutaneously to Wistar rats once daily for seven days, starting two to six hours after spinal cord injury caused by a fall of weight. Compared to untreated animals, treated rats recovered better walking ability, lost fewer motor neurons and had lower levels of TNF-α (a pro-inflammatory signal) and caspase-3. At the same time, the mRNA level of CD206, a marker of pro-aging M2 macrophages, increased. Tissue examinations showed smaller areas of damage. Overall, the treatment changed the immune response from a damaging M1-type activity to a protective M2-type activity, with both functional and structural benefits [54].
Protection after traumatic brain injury (TBI)
Ac-SDKP helps protect the brain and promotes brain repair when administered soon after injury. Zhang et al (2017) induced controlled cortical injuries in rats and administered this agent (0.8 mg/kg/day) to them via minipump for three days, starting one hour after injury. From day 7 to day 35, sensory-motor test scores improved, and on days 33-35 spatial learning was also better compared to the control group (p < 0.05). By the end of the study, the amount of cortical damage and loss of hippocampal neurons had decreased, while blood vessel growth, new neuron formation and dendritic spike density were higher. Early treatment also reduced fibrin accumulation and attenuated immune cell activation. Mechanistic tests showed that blocking TGF-β1/NF-κB signalling explained much of the anti-inflammatory effect [55].
Benefits in a disease similar to multiple sclerosis (MS)
It also reduces brain stress and inflammation in models of multiple sclerosis. Pejman et al (2020) subjected C57BL/6 mice to experimental autoimmune encephalomyelitis (EAE). Typically, EAE increases ER stress markers (caspase-12, CHOP, PDI), oxidative stress and immune cell influx into the hippocampus. With treatment, caspase-12 and CHOP levels in oligodendrocytes decreased, caspase-3 activation decreased, ROS oxidation and lipid peroxidation decreased, antioxidant capacity improved and IL-6/IL-1β levels decreased. Brain scans confirmed less damage to the hippocampus and less infiltration of immune cells, indicating slower disease progression [56].
Ac-SDKP for liver health (based on animal studies)
Slowing down chemical-induced liver scarring
The Ac-SDKP peptide helps protect the liver from chemical damage by regulating a key gene control switch and growth pathway. Wei et al. (2022) studied rats with carbon tetrachloride (CCl₄)-induced liver damage and found less death of stellate cells - the main scar-forming cells in the liver. Fibrosis was also reduced. Mechanistic tests showed that the treatment reduced levels of WTAP, the enzyme that adds m⁶A markers to RNA. This change stabilised RNA Ptch1 and adjusted the activity of the Hedgehog pathway, the main driver of scar formation. Overall, the results highlight an anti-fibrotic effect through the WTAP/m⁶A/Ptch1 pathway, which regulates Hedgehog signalling [59].
Protection in fibrosis caused by bile ducts
Ac-SDKP also protects the liver when scarring is caused by biliary blockage. Zhang et al (2012) used the bile duct ligation (BDL) model in rats and treated them continuously for a fortnight. Compared to untreated animals, those that received the peptide had inhibited TGF-β1 signalling and lower levels of markers associated with activated stellate cells (α-SMA, FSP-1). The expression of collagen-related genes (Col I, Col III) and turnover enzymes (MMP-2, TIMP-1, TIMP-2) was also decreased. Blood markers related to liver function improved, with ALT, AST, bilirubin and prothrombin time approaching normal. On tissue preparations, fewer mast cells, less collagen accumulation and an overall reduction in fibrosis and inflammation were observed [60].
Maintenance of natural defence and repair signals
It helps the liver to maintain its natural resistance during prolonged chemical damage. Chen et al (2010) found that with continuous exposure to CCl₄, natural levels of the peptide decreased over time. Replacing it by infusion (800 µg/kg/day for eight weeks) maintained baseline levels and reduced liver damage, inflammation and fibrosis. Liver enzyme levels in the blood decreased, CD45⁺ inflammatory cells decreased.
, and collagen and α-SMA deposits decreased. Pro-fibrotic signals, such as TGF-β1 and phospho-Smad2/3, decreased, while repair-related signals, BMP-7 and phospho-Smad1/5/8, increased. In cellular assays, it directly blocked the activation of stellate cells, confirming an anti-fibrotic effect at the cellular level [61].
Ac-SDKP for skin and tissue repair (based on animal studies) H3. Hydrogel skin adhesive to accelerate healing and reduce scarring
A special cellulose-based skin adhesive (Dopa-OCMC-PAA, compared to OCMC-PAA) was developed to carry and release Ac-SDKP. Both versions showed good swelling and degradation profiles, high mechanical strength and safety for use with cells, but Dopa-OCMC-PAA performed best. In mice with liver bleeding, this adhesive stopped bleeding faster. In tests on fibroblasts, it increased the levels of enzymes responsible for tissue remodelling (MMP-1 and MMP-3), while decreasing the activity of collagen genes. In rabbits with thickened ear scars, Dopa-OCMC-PAA combined with a peptide reduced scar scores, decreased cell counts, improved collagen structure and again showed higher levels of MMP-1/MMP-3 with less collagen gene activity. In summary, these results showed better wound healing and less scarring [62].
Topical application improves skin survival and repair
In skin flap surgeries in rats (abdominal and dorsal), injections of Ac-SDKP at a dose of 5 µg/kg twice daily for three days increased the survival of healthy skin. The area of viable flap increased from 50.9 ± 19.3% to 66.4 ± 7.5% for ventral flaps and from 53.4 ± 4.2% to 74.7 ± 6.6% for dorsal flaps. For UVB-damaged skin tissue, topical application improved survival. Topical application also accelerated new skin growth, increased keratin-14 levels (a marker of skin-building cells) and increased fibronectin levels, demonstrating its role in the development and repair of blood vessels [63].
Protecting blood formation during chemotherapy
In mice receiving the chemotherapy drug doxorubicin, administration of Ac-SDKP at a dose of 2.4 µg/day (continuous or divided) starting 48 hours before treatment reduced mortality and protected the stem cells responsible for blood formation (LTRC, CFU-S, HPP-CFC and CFU-GM). The addition of G-CSF further accelerated the recovery of CFU-GM. Timing of administration was crucial - to protect against short-term marrow damage and long-term stem cell loss, it was necessary to start administration before chemotherapy [64].
More potent anti-fibrotic activity due to improved analogues and combination of ACE inhibitors
In experiments with lung fibroblasts, the ACE-resistant form of Ac-SDKP reduced scarring signals (TGF-β/Smad3) and collagen accumulation better than the natural form. The shortened fragment (Ac-DKP) had only a weak effect and was slowly degraded by ACE. In combination with ACE inhibitors, the peptide inhibited hydroxyproline (a marker of collagen) more than alone, showing a stronger effect and clinical potential. At doses of 10-⁶ to 10-¹⁷ M, both thymosin-β4 (Tβ4) and the peptide reduced mast cell growth (best at 10-¹⁴ M) and induced unusual nuclear changes associated with cell cycle arrest. At a concentration of 10-⁸ M, they also induced the release of chemicals from mast cells (degranulation), with the peptide showing a stronger effect (~89%) than Tβ4 (~57%). Other Tβ4 fragments showed no effect, demonstrating that the effect was specific to intact Tβ4 and the peptide [65, 66].
Ac-SDKP dose
In preclinical studies, Ac-SDKP is most often administered subcutaneously via minipump at a dose of approximately 0.8 mg/kg/day to reduce fibrosis and inflammation in the heart/vasculature and kidneys. In studies in mice after myocardial infarction, a dose of 1.6 mg/kg/day is sometimes used to provide early protection. In brain/neurons, a dose of approximately 0.8 mg/kg/day for 3-7 days is usually used in short cycles starting within hours of injury. In cellular studies it is common to pre-treat with a dose of around 10 nM. In the liver in anti-fibrotic protocols, a dose of approximately 0.8 mg/kg/day is often given during chronic injury. In the lung, the bleomycin model used a dose of 0.6 mg/kg intraperitoneally with repeated doses starting on day 0 or day 7. In skin/wound repair, topical dosing included 5 µg/kg per injection twice daily for three days or hydrogels containing peptides for topical release. In haematology/bone marrow repair, very low microgram doses are used, such as 2.4 µg/day in mice prior to chemotherapy and short treatments of µg/kg/day in early clinical trials.
Disclaimer
This article has been written for educational purposes and is intended to raise awareness of the substance under discussion. It is important to note that the article is about the substance in general - it is not a description of a specific product (chemical reagent). We are not suggesting the use of chemical reagents on humans - this is prohibited by law, for a product to be used for treatment it must be registered as a medicine. The information contained in the text is based on available scientific research and is not intended as medical advice or to promote self-medication. The reader should consult with a qualified health professional for all health and treatment decisions.
References
- Wang, W., Jia, W. and Zhang, C. (2022). The role of Tβ4-POP-Ac-SDKP axis in organ fibrosis. International journal of molecular sciences, 23(21), 13282. https://doi.org/10.3390/ ijms232113282
- Nakagawa, P., Romero, C. A., Jiang, X., D'Ambrosio, M., Bordcoch, G., Peterson, E. L., Harding, P., Yang, X. P. and Carretero, O. A. (2018). Ac-SDKP reduces mortality and cardiac rupture risk after acute myocardial infarction. PLoS One, 13(1), e0190300. https://doi.org/10.1371/ journal.pone.0190300 https://pubmed.ncbi.nlm.nih.gov/29364896/
- Peng, H., Carretero, O. A., Brigstock, D. R., Oja-Tebbe, N. and Rhaleb, N. E. (2003). Ac-SDKP reverses cardiac fibrosis in rats with renal vascular hypertension. Hypertension, 42(6), 1164–1170. https://doi.org/10.1161/01.HYP.0000100423.24330.96 https://pubmed.ncbi.nlm.nih.gov/14581293/
- Yang, F., Yang, X. P., Liu, Y. H., Xu, J., Cingolani, O., Rhaleb, N. E., & Carretero, O. A. (2004). Ac-SDKP reverses inflammation and fibrosis in rats with heart failure after myocardial infarction. Hypertension, 43(2), 229-236. https://doi.org/10.1161/01.HYP.0000107777.91185.89 https:// pubmed.ncbi.nlm.nih.gov/14691195/
- Rasoul, S., Carretero, O. A., Peng, H., Cavasin, M. A., Zhuo, J., Sanchez-Mendoza, A., Brigstock,
D. R. and Rhaleb, N. E. (2004). Anti-fibrotic effects of Ac-SDKP and angiotensin-converting enzyme inhibition in hypertension. Journal of Hypertension, 22(3), 593-603. https://doi.org/ 10.1097/00004872-200403000-00023 https://pubmed.ncbi.nlm.nih.gov/15076166/
- Rhaleb, N. E., Peng, H., Harding, P., Tayeh, M., LaPointe, M. C. and Carretero, O. A. (2001). Effects of N-acetyl-seryl-aspartyl-lysyl-proline on DNA and collagen synthesis in rat cardiac fibroblasts. Hypertension, 37 (3), 827-832. https://doi.org/10.1161/01.hyp.37.3.827 https:// pubmed.ncbi.nlm.nih.gov/11244003/
- Liu, Y.-H., D'Ambrosio, M., Liao, T.-D., Peng, H., Rhaleb, N.-E., Sharma, U., André, S., Gabius, H.-J. and Carretero, O. A. (2009). N-acetyl-seryl-aspartyl-lysyl-proline prevents cardiac remodelling and dysfunction induced by galectin-3, a lectin that regulates adhesion/growth in mammals. American Journal of Physiology-Heart and Circulatory Physiology, 296(2), H404-H412. https://doi.org/ 10.1152/ajpheart.00747.2008 https://pubmed.ncbi.nlm.nih.gov/19098114/
- Rhaleb, N. E., Peng, H., Yang, X. P., Liu, Y. H., Mehta, D., Ezan, E. and Carretero, O. A. (2001). Long-term effects of N-acetyl-seryl-aspartyl-lysyl-proline on left ventricular collagen deposition in rats with hypertension caused by damage to two kidneys and clamping of one of them. Circulation, 103(25), 3136-3141. https://doi.org/ 10.1161/01.cir.103.25.3136 https://pubmed.ncbi.nlm.nih.gov/11425781/
- Cavasin M. A. (2006). Therapeutic potential of thymosin beta4 and its N-acetyl-seryl-aspartyl-lysyl-proline (Ac-SDKP) derivative in the treatment of the heart after myocardial infarction. American journal of cardiovascular drugs : drugs, devices, and other interventions, 6(5), 305-311. https://doi.org/ 10.2165/00129784-200606050-00003 https://pubmed.ncbi.nlm.nih.gov/17083265/
- Rhaleb, N. E., Pokharel, S., Sharma, U. C., Peng, H., Peterson, E., Harding, P., Yang, X. P. and Carretero, O. A. (2013). N-acetyl-Ser-Asp-Lys-Pro inhibits matrix metalloproteinase activation by interleukin-1β in cardiac fibroblasts. Pflügers Archiv - European Journal of
Physiology, 465(10), 1487-1495. https://doi.org/10.1007/s00424-013-1262-8 https:// pubmed.ncbi.nlm.nih.gov/23652767/
- Nakagawa, P., Liu, Y., Liao, T. D., Chen, X., González, G. E., Bobbitt, K. R., Smolarek, D., Peterson, E. L., Kedl, R., Yang, X. P., Rhaleb, N. E. and Carretero, O. A. (2012). N-acetyl-seryl-aspartyl-lysyl-proline treatment prevents experimental autoimmune myocarditis in rats. American Journal of Physiology-Heart and Circulatory Physiology, 303(9), H1114-H1127. https:// doi.org/10.1152/ajpheart.00300.2011 https://pubmed.ncbi.nlm.nih.gov/22923621/
- González, G. E., Rhaleb, N. E., Nakagawa, P., Liao, T. D., Liu, Y., Leung, P., Dai, X., Yang, X. P. and Carretero, O. A. (2014). N-acetyl-seryl-aspartyl-lysyl-proline reduces cardiac collagen cross-linking and inflammation in angiotensin II-induced hypertensive rats. Clinical Science, 126(1), 85-
- Peng, H., Xu, J., Yang, X. P., Kassem, K. M., Rhaleb, I. A., Peterson, E. and Rhaleb, N. E. (2019). N-acetyl-seryl-aspartyl-lysyl-proline treatment protects the heart from excessive myocardial damage and heart failure in mice. Canadian Journal of Physiology and Pharmacology, 97(8), 753-765. https://doi.org/10.1139/cjpp-2019-0047 https://pubmed.ncbi.nlm.nih.gov/30998852/
- Castoldi, G., di Gioia, C. R. T., Bombardi, C., Perego, C., Perego, L., Mancini, M., Leopizzi, M., Corradi, B., Perlini, S., Zerbini, G. and Stella, A. (2009). Prevention of myocardial fibrosis by N-acetyl-seryl-aspartyl-lysyl-proline in diabetic rats. Clinical Science, 118(3), 211-220. https:// doi.org/10.1042/cs20090234 https://pubmed.ncbi.nlm.nih.gov/20310083/
- Sharma, U. C., Sonkawade, S. D., Baird, A., Chen, M., Xu, S., Sexton, S., Singh, A. K., Groman, A., Turowski, S. G., Spernyak, J. A., Mahajan, S. D. and Pokharel, S. (2018). Effects of a novel Ac-SDKP peptide on radiation-induced coronary endothelial damage and resting myocardial blood flow. Cardio-Oncology, 4, 8. https://doi.org/10.1186/s40959-018-0034-1 https:// pubmed.ncbi.nlm.nih.gov/31057947/
- Suhail, H., Peng, H., Matrougui, K. and Rhaleb, N. E. (2024). Ac-SDKP attenuates ER stress-stimulated collagen production in cardiac fibroblasts through CHOP-mediated inhibition of NF-κB expression. Frontiers in Pharmacology, 15, 1352222. https://doi.org/10.3389/fphar.2024.1352222 https://pubmed.ncbi.nlm.nih.gov/38495093/
- Zhu, L., Yang, X. P., Janic, B., Rhaleb, N. E., Harding, P., Nakagawa, P., Peterson, E. L. and Carretero, O. A. (2016). Ac-SDKP inhibits TNF-α-induced ICAM-1 expression in endothelial cells through inhibition of IκB kinase and NF-κB activation. American Journal of Physiology-Heart and Circulatory Physiology, 310(9), H1176-H1183. https://doi.org/10.1152/ajpheart.00252.2015 https://pubmed.ncbi.nlm.nih.gov/26945075/
- Lin, C. X., Rhaleb, N. E., Yang, X. P., Liao, T. D., D'Ambrosio, M. A. and Carretero, O. A. (2008). Prevention of aortic fibrosis by N-acetyl-seryl-aspartyl-lysyl-proline in angiotensin II-induced hypertension. American Journal of Physiology-Heart and Circulatory Physiology, 295(3), H1253-H1261. https://doi.org/10.1152/ajpheart.00481.2008 https://pubmed.ncbi.nlm.nih.gov/18641275/
- Sharma, U. C., Sonkawade, S. D., Spernyak, J. A., Sexton, S., Nguyen, J., Dahal, S., Attwood, K. M., Singh, A. K., van Berlo, J. H. and Pokharel, S. (2018). The small peptide Ac-SDKP inhibits the
radiation-induced cardiomyopathy. Circulation: Heart Failure, 11(8), e004867. https://doi.org/ 10.1161/CIRCHEARTFAILURE.117.004867 https://pubmed.ncbi.nlm.nih.gov/30354563/
- Conte, E., Iemmolo, M., Fruciano, M., Fagone, E., Gili, E., Genovese, T., Esposito, E., Cuzzocrea, S. and Vancheri, C. (2015). Effects of thymosin β4 and its N-terminal fragment Ac-SDKP on TGF-β-treated human lung fibroblasts and in a mouse model of bleomycin-induced pulmonary fibrosis. Expert Opinion on Biological Therapy, 15(Suppl 1), S211-S221. https://doi.org/ 10.1517/14712598.2015.1026804 https://pubmed.ncbi.nlm.nih.gov/26098610/
- Liu, S., Jin, R., Zheng, G., Wang, Y., Li, Q., Jin, F., Li, Y., Li, T., Mao, N., Wei, Z., Li, G., Fan, Y.,
Xu, H., Li, S. and Yang, F. (2023). Ac-SDKP promotes KIF3A-mediated β-catenin inhibition through a ciliary mechanism to limit silica-induced epithelial-myofibroblastic transformation. Biomedicine & Pharmacotherapy, 166, 115411. https://doi.org/10.1016/j.biopha.2023.115411 https://pubmed.ncbi.nlm.nih.gov/37651800/
- Cai, J., Chen, Q., Mehrabi Nasab, E. and Athari, S. S. (2022). Immunomodulatory effects of N-acetyl-seryl-aspartyl-proline and vasoactive intestinal peptide on the pathophysiology of chronic obstructive pulmonary disease. Fundamental & Clinical Pharmacology, 36(6), 1005-1010. https:// doi.org/10.1111/fcp.12811 https://pubmed.ncbi.nlm.nih.gov/35763864/
- Wang, J., Qian, Y., Gao, X., Mao, N., Geng, Y., Lin, G., Zhang, G., Li, H., Yang, F. and Xu, H. (2020). Synthesis and identification of a novel Ac-SDK (biotin) proline peptide that can induce anti-fibrotic effects in rats suffering from silicosis. Drug design, development and therapy, 14, 4315–4326. https://doi.org/10.2147/DDDT.S262716 https://pubmed.ncbi.nlm.nih.gov/33116418/
- Conte, E., Fagone, E., Gili, E., Fruciano, M., Iemmolo, M., Pistorio, M. P., Impellizzeri, D., Cordaro, M., Cuzzocrea, S., & Vancheri, C. (2016). Preventive and therapeutic effects of the N-terminal thymosin β4 fragment Ac-SDKP in a bleomycin-induced pulmonary fibrosis model. Oncotarget, 7(23), 33841-33854. https://doi.org/10.18632/oncotarget.8409 https:// pubmed.ncbi.nlm.nih.gov/27029074/
- Cao, W., Yao, S. S., Gong, H. B., Zhu, L. Y., Miao, Z. Y. and Deng, H. J. (2022). Regulatory effect of Ac-SDKP on the phosphorylated heat shock protein 27/SNAI1 pathway in rats with silicosis. Zhonghua Lao Dong Wei Sheng Zhi Ye Bing Za Zhi, 40(2), 90-96. https://doi.org/10.3760/ cma.j.cn121094-20201218-00702 https://pubmed.ncbi.nlm.nih.gov/35255573/
- Gong, H. B., Zhang, C. M., Tang, X. Y., Gong, R. B., Miao, Z. Y. and Deng, H. J. (2023). Meta-analysis of inhibition of pulmonary fibrosis by Ac-SDKP in animal models. Zhonghua Lao Dong Wei Sheng Zhi Ye Bing To Zhi, 41 (4), 262-270. https://doi.org/10.3760/ cma.j.cn121094-20211115-00565 https://pubmed.ncbi.nlm.nih.gov/37248179/
- Li, Q., Yang, F., Zhang, L.-J., Yan, J.-B., Chen, P., Li, D.-D. and Wu, K.-F. (2009). [Anti-fibrotic effect of N-acetyl-seryl-aspartyl-lysyl-proline via regulating the expression of transforming growth factor beta and connective tissue growth factor in rats with silicosis]. Zhonghua Lao Dong Wei Sheng Zhi Ye Bing Za Zhi, 27(7), 390-394. PMID: 20039536 https:// pubmed.ncbi.nlm.nih.gov/20039536/
28.Yan, J.-B., Zhang, L.-J. and Li, Q. (2008). [Antifibrotic effect of N-acetyl-seryl-aspartyl-lysyl-proline in lungs of rats with silicosis]. Zhonghua Lao Dong Wei Sheng Zhi Ye Bing Za Zhi, 26(7), 401-405. PMID: 19080377 https://pubmed.ncbi.nlm.nih.gov/19080377/
- Jin, F., Geng, F., Xu, D., Li, Y., Li, T., Yang, X., Liu, S., Zhang, H., Wei, Z., Li, S., Gao, X., Cai, W.,
Mao, N., Yi, X., Liu, H., Sun, Y., Yang, F. and Xu, H. (2021). Ac-SDKP attenuates the activation of pulmonary macrophages and bone osteoclasts in silica-exposed rats by inhibiting TLR4 and RANKL signalling pathways. Journal of Inflammation Research, 14, 1647-1660. https://doi.org/10.2147/ JIR.S306883 https://pubmed.ncbi.nlm.nih.gov/33948088/
- Xu, H., Yang, F., Sun, Y., Yuan, Y., Cheng, H., Wei, Z., Li, S., Cheng, T., Brann, D. and Wang, R. (2012). A novel anti-fibrotic target of Ac-SDKP: inhibition of myofibroblast differentiation in lungs of rats with silicosis. PLoS One, 7(7), e40301. https://doi.org/10.1371/journal.pone.0040301 https:// pubmed.ncbi.nlm.nih.gov/22802960/
- Wang, X., Liu, Y., Xu, H., Zhang, X., Li, S., Xu, D., Gao, X., Zhang, L., Zhang, B., Wei, Z., Wang, R., Brann, D. and Yang, F. (2016). Acetylated α-tubulin regulated by N-acetyl-seryl-aspartyl-lysyl-proline (Ac-SDKP) exerts antifibrotic effects in silica-induced rat pulmonary fibrosis. Scientific Reports, 6, 32257. https://doi.org/10.1038/srep32257 https://pubmed.ncbi.nlm.nih.gov/27577858/
- Deng, H., Xu, H., Zhang, X., Sun, Y., Wang, R., Brann, D. and Yang, F. (2016). Protective effect of Ac-SDKP on follicular epithelial cells via TGF-β1/ROCK1 pathway-mediated EMT inhibition in silicosis in rats. Toxicology and applied pharmacology, 294, 1-10. https://doi.org/10.1016/ j.taap.2016.01.010 https://pubmed.ncbi.nlm.nih.gov/26785300/
- Zhang, L., Xu, D., Li, Q., Yang, Y., Xu, H., Wei, Z., Wang, R., Zhang, W., Liu, Y., Geng, Y., Li, S., Gao, X. and Yang, F. (2018). N-acetyl-seryl-aspartyl-lysyl-proline (Ac-SDKP) alleviates silicotic fibrosis by inhibiting type II alveolar epithelial cell apoptosis via mediating endoplasmic reticulum stress. Toxicology and applied pharmacology, 350, 1-10. https://doi.org/10.1016/ j.taap.2018.04.025 https://pubmed.ncbi.nlm.nih.gov/29684394/
- Nakagawa, P., Masjoan-Juncos, J. X., Basha, H., Janic, B., Worou, M. E., Liao, T. D., Romero, C. A., Peterson, E. L. and Carretero, O. A. (2017). Effects of N-acetyl-seryl-aspartyl-lysyl-proline on blood pressure, renal damage and mortality in systemic lupus erythematosus. Physiological Reports, 5(2), e13084. https://doi.org/10.14814/phy2.13084 https://pubmed.ncbi.nlm.nih.gov/ 28126732/
- Worou, M. E., Liao, T. D., D'Ambrosio, M., Nakagawa, P., Janic, B., Peterson, E. L., Rhaleb, N. E. and Carretero, O. A. (2015). Protective effects of N-acetyl-seryl-aspartyl-lysyl-proline on the kidney in Dahl salt-sensitive rats. Hypertension, 66(4), 816-822. https://doi.org/10.1161/ HYPERTENSIONAHA.115.05970 https://pubmed.ncbi.nlm.nih.gov/26324505/
- Liao, T. D., Nakagawa, P., Janic, B., D'Ambrosio, M., Worou, M. E., Peterson, E. L., Rhaleb, N. E., Yang, X. P. and Carretero, O. A. (2015). N-Acetyl-Seryl-Aspartyl-Lysyl-Proline: mechanisms of renal protection in a mouse model of systemic lupus erythematosus. American Journal of Physiology-Renal Physiology, 308 (10), F1146-F1154. https://doi.org/10.1152/ajprenal.00039.2015 https://pubmed.ncbi.nlm.nih.gov/25740596/
37.Rhaleb, N. E., Pokharel, S., Sharma, U. and Carretero, O. A. (2011). Renal protective effects of N-acetyl-Ser-Asp-Lys-Pro in deoxycorticosterone acetate-salt-induced hypertensive mice. Journal of Hypertension, 29(2), 330-338. https://doi.org/10.1097/HJH.0b013e32834103ee https:// pubmed.ncbi.nlm.nih.gov/21052020/
- Shibuya, K., Kanasaki, K., Isono, M., Sato, H., Omata, M., Sugimoto, T., Araki, S., Isshiki, K., Kashiwagi, A., Haneda, M. and Koya, D. (2005). N-acetyl-seryl-aspartyl-lysyl-proline prevents renal failure and mesangial matrix proliferation in db/db mice with diabetes. Diabetes, 54(3), 838-845. https://doi.org/10.2337/diabetes.54.3.838 https://pubmed.ncbi.nlm.nih.gov/15734863/
- Castoldi, G., di Gioia, C. R. T., Bombardi, C., Preziuso, C., Leopizzi, M., Maestroni, S., Corradi, B., Zerbini, G. and Stella, A. (2013). Antifibrotic effects of N-acetyl-seryl-aspartyl-lysyl-proline on the kidney in diabetic rats. American Journal of Nephrology, 37(1), 65-73. https://doi.org/10.1159/000346116 https://pubmed.ncbi.nlm.nih.gov/23327833/
- Zhang, R., Hu, Z., Wang, Y., Qiu, R., Wang, G., Wang, L. and Hu, B. (2022). Biomimetic double-net hydrogel alleviates renal fibrosis and promotes renal regeneration. Journal of Materials Chemistry B, 10 (45), 9424-9437. https://doi.org/10.1039/d2tb01939f https:// pubmed.ncbi.nlm.nih.gov/36378134/
- Zuo, Y., Chun, B., Potthoff, S. A., Kazi, N., Brolin, T. J., Orhan, D., Yang, H.-C., Ma, L.-J., Kon, V., Myöhänen, T., Rhaleb, N.-E., Carretero, O. A. and Fogo, A. B. (2013). Thymosin β4 and its degradation product, Ac-SDKP, are novel repair agents in renal fibrosis. Kidney International, 84(6), 1166-1175. https://doi.org/10.1038/ki.2013.209 https://pubmed.ncbi.nlm.nih.gov/23739235/
- Wang, M., Liu, R., Jia, X., Mu, S. and Xie, R. (2010). N-acetyl-seryl-aspartyl-lysyl-proline attenuates renal inflammation and tubulointerstitial fibrosis in rats. International Journal of Molecular Medicine, 26 (6), 795-801. https://doi.org/10.3892/ijmm_00000527 https:// pubmed.ncbi.nlm.nih.gov/21042772/
- Liao, T.-D., Yang, X.-P., D'Ambrosio, M., Zhang, Y., Rhaleb, N.-E. and Carretero, O. A. (2010). N-acetyl-seryl-aspartyl-lysyl-proline attenuates renal damage and dysfunction in hypertensive rats with reduced renal mass: Hypertension Research Council. Hypertension, 55(2), 459-467. https://doi.org/10.1161/HYPERTENSIONAHA.109.144568 https://pubmed.ncbi.nlm.nih.gov/ 20026760/
- Peng, H., Carretero, O. A., Raij, L., Yang, F., Kapke, A. and Rhaleb, N. E. (2001). Antifibrotic effects of N-acetyl-seryl-aspartyl-lysyl-proline on heart and kidney in aldosterone-salt-induced hypertensive rats. Hypertension, 37(2 Pt 2), 794-800. https://doi.org/10.1161/01.hyp.37.2.794 https:// pubmed.ncbi.nlm.nih.gov/11230375/
- Omata, M., Taniguchi, H., Koya, D., Kanasaki, K., Sho, R., Kato, Y., Kojima, R., Haneda, M. and Inomata, N. (2006). N-acetyl-seryl-aspartyl-lysyl-proline attenuates the progression of renal dysfunction and fibrosis in WKY rats with established glomerulonephritis. Journal of the American Society of Nephrology, 17(3), 674-685. https://doi.org/10.1681/ ASN.2005040385 https://pubmed.ncbi.nlm.nih.gov/16452498/
- Nagai, T., Kanasaki, M., Srivastava, S. P., Nakamura, Y., Ishigaki, Y., Kitada, M., Shi, S., Kanasaki, K. and Koya, D. (2014). N-acetyl-seryl-aspartyl-lysyl-proline inhibits diabetes-related
diabetes-related renal fibrosis and endothelial-mesenchymal transition. BioMed Research International, 2014, 696475. https://doi.org/10.1155/2014/696475 https://pubmed.ncbi.nlm.nih.gov/24783220/
- Srivastava, S. P., Goodwin, J. E., Kanasaki, K. and Koya, D. (2020). Metabolic reprogramming with N-acetyl-seryl-aspartyl-lysyl-proline protects against diabetic kidney disease. British Journal of Pharmacology, 177 (16), 3691-3711. https://doi.org/10.1111/bph.15087 https:// pubmed.ncbi.nlm.nih.gov/32352559/
- Carde, P., Chastang, C., Goncalves, E., Mathieu-Tubiana, N., Vuillemin, E., Delwail, V., Corbion, O., Vekhoff, A., Isnard, F., Ferrero, J. M., et al. (1992). [Seraspenid (acetylSDKP): A phase I-II clinical trial of a haematopoietic inhibitor protecting against the toxicity of aracycline and ifosfamide monochemotherapy]. Clinical study C R Acad Sci III, 315(13), 545-550. PMID: 1300237 https:// pubmed.ncbi.nlm.nih.gov/1300237/
- Cappelaere, P., Hecquet, B., Rolland, F., Meeus, L., Domenge, C., Krakowski, I., De Gislain, C., Chauvergne, J., Dufour-Esquerré, F., Carde, P. (1995). [Randomised placebo study of bone marrow protection with goralatide in patients with squamous cell carcinoma of the upper respiratory tract and gastrointestinal tract or oesophagus treated with a combination of carboplatin and fluorouracil]. Bull Cancer, 82(9), 732-737. PMID: 8535033 https://pubmed.ncbi.nlm.nih.gov/8535033/
- Nitta, K., Shi, S., Nagai, T., Kanasaki, M., Kitada, M., Srivastava, S. P., Haneda, M., Kanasaki, K. and Koya, D. (2016). Oral administration of N-acetyl-seryl-aspartyl-lysyl-proline ameliorates renal disease in mice with type 1 and type 2 diabetes through a therapeutic regimen. BioMed Research International, 2016 , 9172157 . https://doi.org/10.1155/2016/9172157 https:// pubmed.ncbi.nlm.nih.gov/27088094/
- Tan, H., Zhao, J., Wang, S., Zhang, L., Wang, H., Huang, B., Liang, Y., Yu, X. and Yang, N. (2012). Ac-SDKP attenuates the progression of lupus nephritis in MRL/lpr mice. International Immunopharmacology, 14(4), 401–409. https://doi.org/10.1016/j.intimp.2012.07.023https:// pubmed.ncbi.nlm.nih.gov/22922317/
- Maheshwari, M., Romero, C. A., Monu, S. R., Kumar, N., Liao, T. D., Peterson, E. L. and Carretero,
O. A. (2018). Renal protective effects of N-acetyl-seryl-aspartyl-lysyl-proline (Ac-SDKP) in obese rats on a high-salt diet. American Journal of Hypertension, 31(8), 902-909. https://doi.org/ 10.1093/ajh/hpy052 https://pubmed.ncbi.nlm.nih.gov/29722788/
- Kamarehei, M., & Zahednasab, H. (2025). Neuroprotective effects of Ac-SDKP peptide in SH-SY5Y cells and a rat model of Parkinson's disease against 6-OHDA-induced oxidative stress and ER stress. Neuropeptides, 112, 102534. https://doi.org/10.1016/j.npep.2025.102534 https:// pubmed.ncbi.nlm.nih.gov/40544680/
- Hashemizadeh, S., Pourkhodadad, S., Hosseindoost, S., Pejman, S., Kamarehei, M., Badripour, A., Omidi, A., Pestehei, S. K., Seifalian, A. M. and Hadjighassem, M. (2022). Ac-SDKP peptide improves functional recovery after spinal cord injury in a preclinical model. Neuropeptides, 92, 102228. https://doi.org/10.1016/j.npep.2022.102228 https://pubmed.ncbi.nlm.nih.gov/ 35101843/
- Zhang, Y., Zhang, Z. G., Chopp, M., Meng, Y., Zhang, L., Mahmood, A. and Xiong, Y. (2017). Treatment of traumatic brain injury in rats with N-acetyl-seryl-aspartyl-lysyl-proline. Journal of
Neurosurgery, 126(3), 782-795. https://doi.org/10.3171/2016.3.JNS152699 http:// pubmed.ncbi.nlm.nih.gov/28245754/
- Pejman, S., Kamarehei, M., Riazi, G., Pooyan, S. and Balalaie, S. (2020). Ac-SDKP attenuates the progression of experimental autoimmune encephalomyelitis by inhibiting ER and oxidative stress in the hippocampus of C57BL/6 mice. Brain Research Bulletin, 154, 21–31. https://doi.org/10.1016/j.brainresbull.2019.09.014 https://pubmed.ncbi.nlm.nih.gov/31589901/
- Zhang, L., Chopp, M., Teng, H., Ding, G., Jiang, Q., Yang, X. P., Rhaleb, N. E. and Zhang, Z. G. (2014). Combination treatment of N-acetyl-seryl-aspartyl-lysyl-proline and tissue plasminogen activator provides potent neuroprotection in rats after stroke. Stroke, 45(4), 1108-1114. https:// doi.org/10.1161/STROKEAHA.113.004399 https://pubmed.ncbi.nlm.nih.gov/24549864/
- Kim, D. H., Moon, E.-Y., Yi, J. H., Lee, H. E., Park, S. J., Ryu, Y.-K., Kim, H.-C., Lee, S. and Ryu, J.
H. (2015). Thymosin β4 peptide fragment enhances neurogenesis in the hippocampus and facilitates spatial memory. Neuroscience, 310, 51-62. https://doi.org/10.1016/j.neuroscience.2015.09.017 https://pubmed.ncbi.nlm.nih.gov/26363149/
- Wei, A., Zhao, F., Hao, A., Liu, B. and Liu, Z. (2022). N-acetyl-seryl-aspartyl-lysyl-proline (AcSDKP) attenuates liver fibrosis via the WTAP/m6A/Ptch1 axis via the Hedgehog pathway. Gene, 813, 146125. https://doi.org/10.1016/j.gene.2021.146125 https://pubmed.ncbi.nlm.nih.gov/34921949/
- Zhang, L., Xu, L. M., Chen, Y. W., Ni, Q. W., Zhou, M., Qu, C. Y. and Zhang, Y. (2012). Antifibrotic effect of N-acetyl-seryl-aspartyl-lysyl-proline on liver fibrosis induced by biliary ligation in rats. World Journal of Gastroenterology, 18(37), 5283-5288. https://doi.org/10.3748/wjg.v18.i37.5283 https://pubmed.ncbi.nlm.nih.gov/23066324/
- Chen, Y. W., Liu, B. W., Zhang, Y. J., Chen, Y. W., Dong, G. F., Ding, X. D., Xu, L. M., Pat, B.,
Fan, J. G. and Li, D. G. (2010). Preservation of basal levels of AcSDKP attenuates carbon tetrachloride-induced liver fibrosis in rats. Journal of Hepatology, 53(3), 528-536. https://doi.org/10.1016/ j.jhep.2010.03.027 https://pubmed.ncbi.nlm.nih.gov/20646773/
- Ameri, Z., Shahabi, A., Farsinejad, A., Sattarzadeh Bardsiri, M., Javedani, H., Bagher, Z., Saraee, A. and Brouki Milan, P. (2025). Cellulose-based adhesive hydrogel containing N-acetyl-seryl-aspartyl-lysyl-proline peptide to accelerate wound healing and prevent scarring in an in vivo rabbit ear scar model. International Journal of Biological Macromolecules, 322(Pt 1), 144981. https:// doi.org/10.1016/j.ijbiomac.2025.144981 https://pubmed.ncbi.nlm.nih.gov/40480579/
- Fromes, Y., Liu, J. M., Kovacevic, M., Bignon, J. and Wdzieczak-Bakala, J. (2006). Acetyl-serine-asparaginyl-lysine-proline tetrapeptide improves skin flap survival and accelerates wound healing. Wound Repair and Regeneration, 14 (3), 306-312. https://doi.org/10.1111/ j.1743-6109.2006.00125.x https://pubmed.ncbi.nlm.nih.gov/16808809/
- Massé, A., Ramirez, L. H., Bindoula, G., Grillon, C., Wdzieczak-Bakala, J., Raddassi, K., Deschamps de Paillette, E., Mencia-Huerta, J. M., Koscielny, S., Potier, P., Sainteny, F. and Carde,
P. (1998). Acetyl-N-Ser-Asp-Lys-Pro tetrapeptide (Goralatide) protects against doxorubicin-induced toxicity: improved mouse survival and protection of bone marrow stem and progenitor cells. Blood, 91(2), 441-449. PMID: 9427696 https://pubmed.ncbi.nlm.nih.gov/9427696/
65.Ramasamy, V., Ntsekhe, M. and Sturrock, E. (2021). Investigating the anti-fibrotic potential of peptides with an N-acetyl-seryl-aspartyl-lysyl-proline sequence. Clinical and Experimental Pharmacology and Physiology, 48(11), 1558-1565. https://doi.org/10.1111/1440-1681.13565 https:// pubmed.ncbi.nlm.nih.gov/34347311/
- Leeanansaksiri, W., DeSimone, S. K., Huff, T., Hannappel, E. and Huff, T. F. (2004). Thymosin beta
4 and its N-terminal tetrapeptide, AcSDKP, inhibit proliferation and induce dysplastic, non-apoptotic nuclei and mast cell degranulation. Chemistry & Biodiversity, 1(7), 1091–1100. https://doi.org/10.1002/cbdv.200490081 https://pubmed.ncbi.nlm.nih.gov/17191900/